ECG criteria
- New ST-segment elevation at the J-point ≥1 mm (0.1 mV) in two contiguous leads among II, III, and aVF—regardless of sex and age; evaluate in the absence of conditions mimicking STEMI and within the clinical context
- For comparison: in leads V2–V3, the ST-elevation threshold differs and depends on sex and age—at least 1.5 mm in women, at least 2 mm in men aged 40 years and older, and at least 2.5 mm in men younger than 40 years; in all other leads (including II, III, and aVF), at least 1 mm in two contiguous leads
- Reciprocal ST depression in aVL often supports the diagnosis of inferior STEMI, but its absence does not rule out infarction—it may be absent, especially with circumflex artery occlusion; depression in lead I is less common and less pronounced
- The ST III/II ratio and depression in leads I/aVL help suggest the likely culprit artery, but are not a strict diagnostic rule—the culprit artery is definitively determined by coronary angiography
- ST elevation in lead III greater than in II, with marked depression in I and aVF — more commonly corresponds to right coronary artery occlusion; ST in II ≥ ST in III with elevation in I and aVL — more frequently seen with circumflex branch occlusion
- Pathological Q or QS waves in two contiguous inferior leads support the diagnosis of past or evolving myocardial infarction, but are not mandatory and may appear early during acute ischemia; as a reference point — Q ≥0.03 s and ≥1 mm or QS, taking into account normal variants and serial ECG changes
- Acquire right-sided chest leads V3R–V4R if right ventricular involvement is suspected — ST elevation ≥1 mm supports the diagnosis of RV infarction
- In the presence of ST depression in V1–V3, tall R waves, or clinical suspicion of a posterior myocardial infarction, record leads V7–V9; ST elevation ≥0.5 mm in two contiguous posterior leads supports posterior STEMI, taking into account sex, age, and clinical presentation
- Evaluate AV conduction and rhythm — sinus bradycardia and various degrees of AV block are frequently observed
What it looks like on ECG
The primary sign is ST-segment elevation, convex or upsloping, in leads II, III, and aVF. It is frequently accompanied by reciprocal ST depression in aVL, which supports the diagnosis of an ischemic rather than pericarditic ST elevation, although the absence of such depression does not rule out infarction. Depression in lead I is less common and less pronounced.
The ratio of ST elevation in lead III to II helps suggest the likely culprit artery, but it is definitively determined by coronary angiography:
| Pattern | Likely culprit artery |
|---|---|
| ST in III > ST in II, marked depression in I and aVL | most commonly the right coronary artery |
| ST in II ≥ ST in III, elevation also in I, aVL | most commonly the circumflex branch of the left coronary artery |
Proximal occlusion of the right coronary artery frequently involves the right ventricle simultaneously — leads V3R–V4R are required. In the presence of ST depression and tall R waves in V1–V3 (mirror image of posterior ST elevation) or clinical suspicion of a posterior infarction, leads V7–V9 should be recorded.
The dynamic evolution may follow this sequence: hyperacute T waves → ST elevation → pathological Q wave formation → ST resolution → T-wave inversion. The timing and order of this evolution are variable and depend on the duration of occlusion, collateral blood flow, and reperfusion — dating an infarction solely based on ECG morphology without clinical correlation, serial ECGs, and cardiac troponin is not appropriate.
Real ECGs: 8 examples
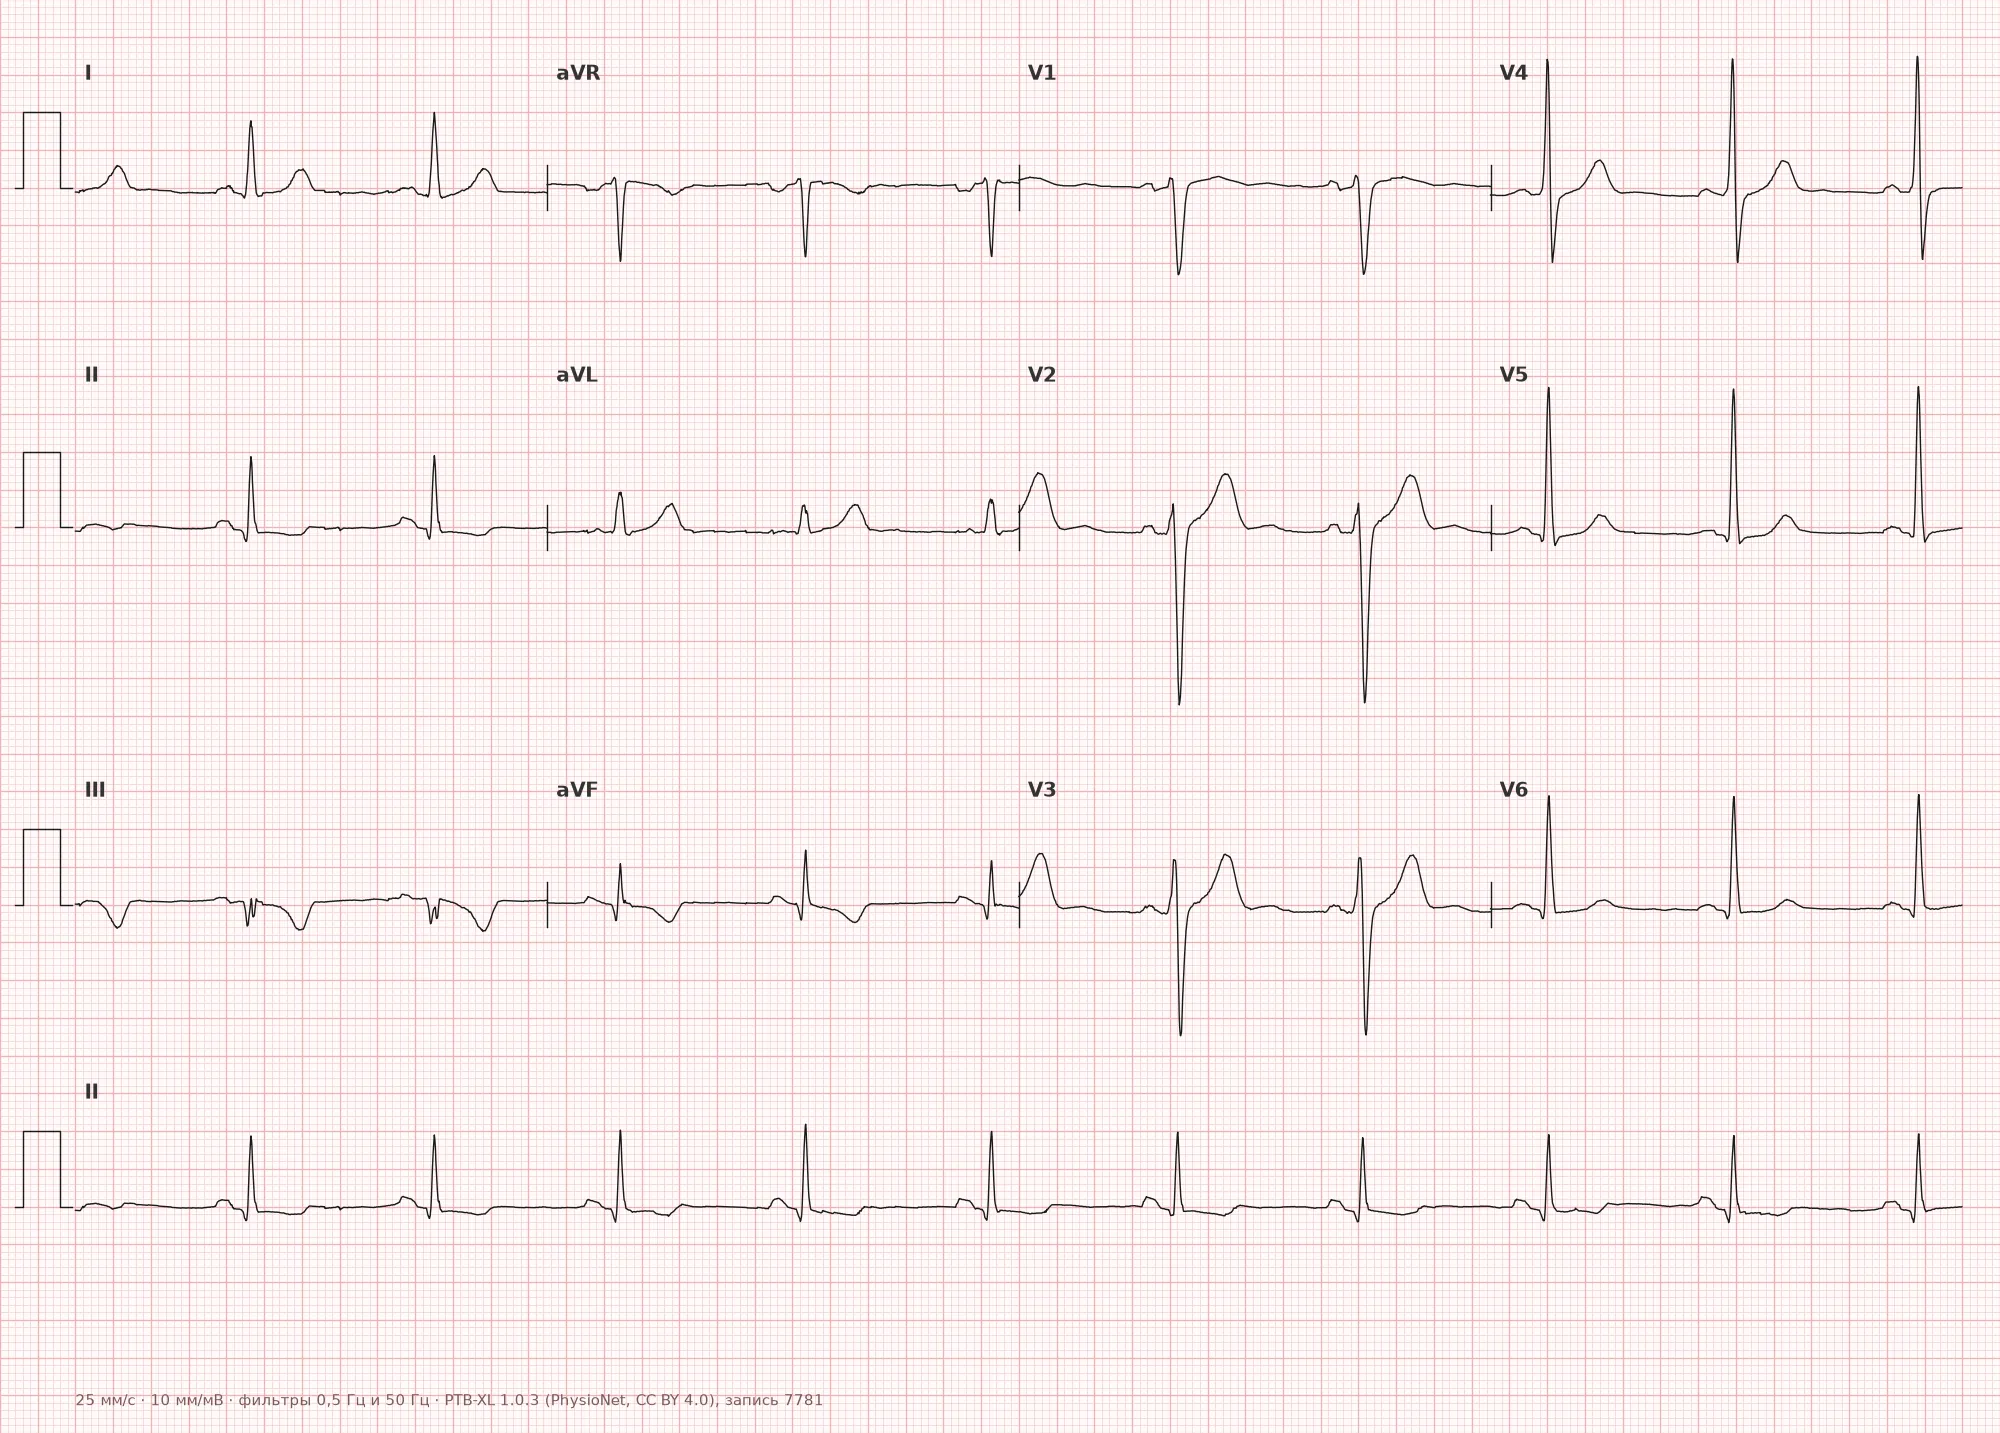
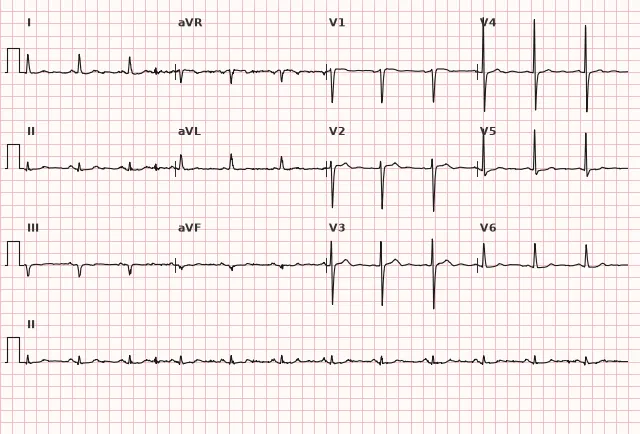
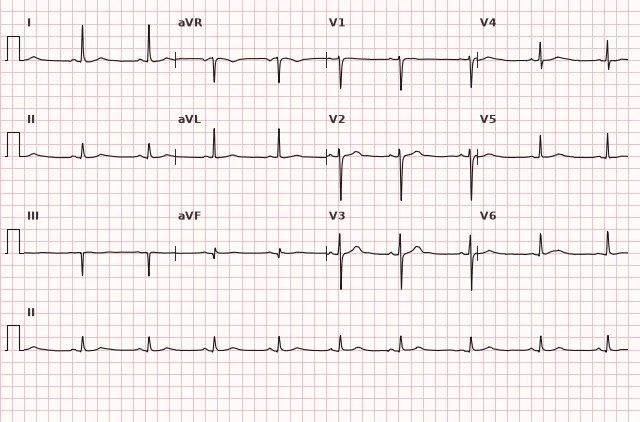
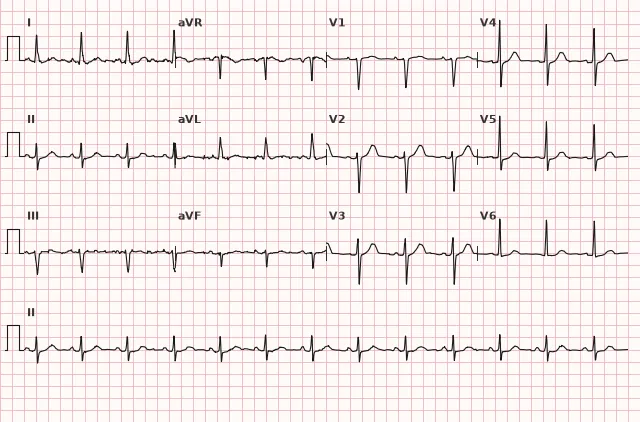
ECG from the open PTB-XL dataset (Wagner P. et al., Scientific Data, 2020; PhysioNet), CC BY 4.0 license. Rendering by WhiteCoat Pro.
Mechanism
The inferior wall of the left ventricle is supplied in the majority of cases by the right coronary artery (right-dominant circulation), and less frequently by the circumflex branch of the left coronary artery (left-dominant circulation). Thrombotic occlusion leads to acute injury and subsequent myocardial necrosis. The injury vector is directed inferiorly, shifting the electromotive force away from leads II, III, and aVF (positive deflection) and typically opposite to aVL (negative deflection, reciprocal depression). The right coronary artery frequently supplies both the sinus and AV nodes, which explains the frequent bradyarrhythmias and AV blocks seen in inferior MI.
Causes
- Thrombotic occlusion of the right coronary artery (most common)
- Thrombotic occlusion of the circumflex branch of the left coronary artery
- Coronary artery spasm (Prinzmetal variant)
- Coronary artery dissection
- Coronary embolism
- Multivessel coronary artery disease with acute decompensation of blood flow
Differential diagnosis
- Pericarditis: diffuse, concordant ST elevation, typically without localized reciprocal changes (except in aVR and sometimes V1), frequently with PR depression
- Early repolarization: ST elevation with a characteristic notched QRS-ST transition, stable pattern without dynamic evolution, absence of reciprocal changes and Q waves
- Brugada syndrome and other patterns involve the right precordial leads rather than the inferior wall
- Inferior-lateral myocardial infarction — inferior leads accompanied by changes in I, aVL, V5–V6
- Hyperkalemia can mimic or alter the ischemic pattern, including pseudo-ST elevation, tall peaked T waves, and QRS widening; such a combination requires urgent electrolyte assessment and clinical correlation, and in cases of suspected acute occlusion, treatment as STEMI without delaying reperfusion
Clinical significance and management
Inferior STEMI is an indication for immediate activation of the reperfusion network. Primary PCI is preferred if wire crossing is anticipated within 120 minutes of STEMI diagnosis. If primary PCI is not feasible within 120 minutes, symptoms began typically within 12 hours, and there are no contraindications — immediate fibrinolysis should be considered with mandatory transfer to a PCI-capable center: rescue PCI for failed reperfusion, and routine coronary angiography/PCI generally within 2–24 hours after successful lysis.
It is advisable to record right-sided chest leads (V3R–V4R) when right ventricular involvement is suspected, and posterior leads (V7–V9) if concomitant posterior infarction is suspected — this alters fluid management strategy and prognosis. If right ventricular infarction is suspected, hemodynamics should be assessed: avoid nitrates and other vasodilators in the presence of hypotension or preload-dependent cardiac output, and do not administer them without hemodynamic evaluation. In cases of hypotension without pulmonary edema, cautious fluid challenge may be considered, and ongoing shock requires intensive hemodynamic support.
Continuous rhythm monitoring is required — sinus bradycardia and second- to third-degree AV block are likely, which are often reversible following reperfusion but may necessitate temporary cardiac pacing.
Common interpretation errors
- Evaluating only II, III, aVF and failing to consider indications for V3R–V4R and V7–V9
- Considering the absence of ST depression in aVL as a reason to rule out inferior MI
- Confusing isolated ST elevation in lead III with inferior MI without confirmation in a neighboring contiguous lead (the criterion is at least two contiguous leads)
- Failing to recognize that bradycardia and AV block in inferior MI are frequently reflex-mediated (vagal) or related to AV nodal ischemia rather than permanent damage to the conduction system
- Missing a concomitant posterior infarction because it is only visible as a mirror image on a standard 12-lead ECG
1. Which feature most frequently supports the diagnosis of inferior myocardial infarction as opposed to pericarditis?
Reciprocal depression in aVL frequently accompanies ischemic ST elevation of the inferior wall and is typically absent in pericarditis, although its absence does not rule out infarction.
2. The ratio of ST elevation in which leads more commonly suggests right coronary artery occlusion in inferior MI?
The predominance of ST-segment elevation in III over II with marked depression in I and aVL most commonly corresponds to right coronary artery occlusion, though coronary angiography provides the definitive diagnosis.
3. What additional leads should be recorded in inferior myocardial infarction to detect right ventricular infarction?
Right precordial leads V3R–V4R allow detection of ST-segment elevation when the right ventricle is involved, which alters treatment tactics.
Frequently asked questions
How to distinguish inferior MI from pericarditis on ECG?
In inferior MI, ST elevation is confined to the inferior leads and is frequently accompanied by reciprocal depression in aVL. In pericarditis, ST elevation is typically diffuse and concordant, with no localized reciprocal depression (except in aVR and sometimes V1), and PR depression is often visible.
Why do bradycardia and AV block occur in inferior MI?
The right coronary artery supplies the sinus and AV nodes in the majority of cases, so its occlusion can cause ischemia of the conduction system. Reflex vagal activation from the inferior ventricular wall also plays a role (Bezold-Jarisch reflex).
Why record right precordial leads in inferior MI?
To detect concomitant right ventricular infarction — ST elevation in V3R–V4R. This changes management: when RV MI is suspected, hemodynamics are assessed and nitrates and other preload-reducing drugs are used with caution due to the risk of severe hypotension.
How to determine the culprit artery from the ECG in inferior MI?
If ST elevation in III is higher than in II, with marked depression in I and aVL, right coronary artery occlusion is more commonly suspected. If ST elevation in II is equal to or greater than III with elevation in I and aVL, circumflex artery occlusion is more commonly suspected. These are merely probabilistic signs; coronary angiography determines the culprit artery definitively.
Is isolated inferior MI dangerous compared to anterior MI?
In general, inferior MI without right ventricular involvement and without concomitant posterior or lateral injury carries a more favorable prognosis than anterior MI. However, the addition of RV infarction or multivessel disease significantly increases the risk of complications and mortality.
ECG Course
Interpretation from basics to myocardial infarction — learn to read any ECG using a systematic algorithm.
- Video lessons and theory for every topic
- Simulator case studies under every lesson
- Unlimited ECG simulator practice
- Study guide: "All ECGs in 25 minutes"
ECG Strip Simulator
ECG, radiology, histology, pathomorphology, pharmacology — thousands of flashcards with detailed explanations.
- Real ECG strips, not textbook drawings
- Instant answers and explanations
- Streaks and progress tracking in your dashboard
Related terms
More in the section "Ischemia and Myocardial Infarction"
Sources
- Goldberger's Clinical Electrocardiography, 9th ed.
- Hampton, The ECG Made Easy
- ESC Guidelines for the management of STEMI, 2023
- Orlov V.N., Electrocardiography Guide
Educational material for medical students and physicians. Does not replace clinical guidelines and physical examination; the ECG must always be interpreted in conjunction with the clinical picture.